
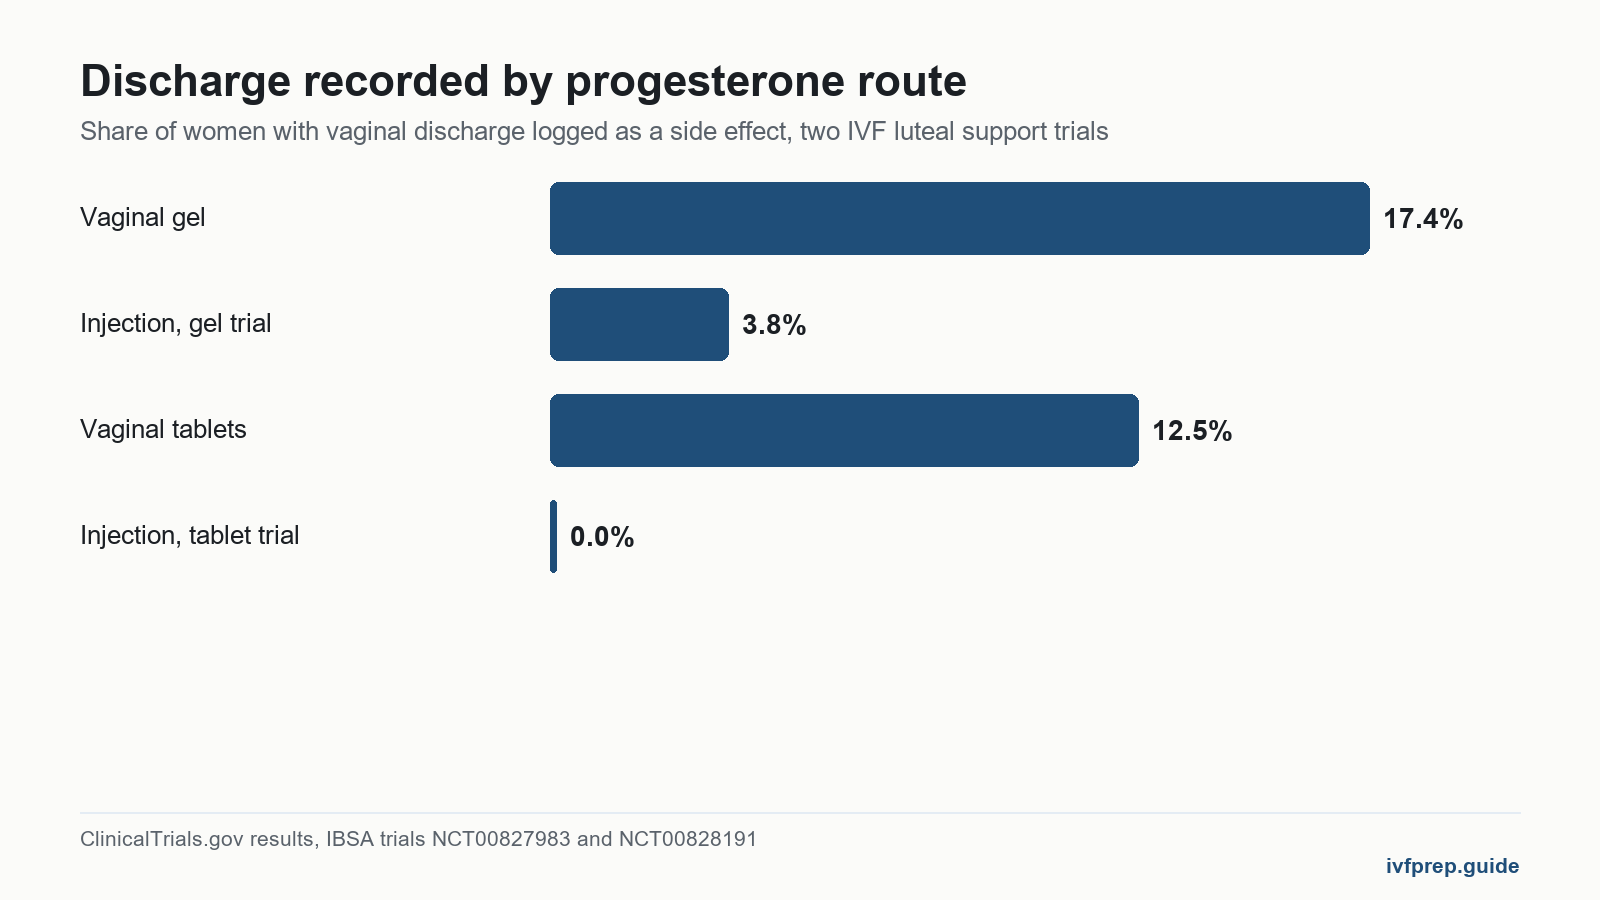
Discharge during implantation is almost always the progesterone, not the embryo. In two IVF trials, discharge was logged for 17 percent of women using a vaginal gel and 12.5 percent using vaginal tablets, against about 4 percent and 0 percent of those given injections. It cannot tell you whether a transfer has worked.
Listen to this article, about 11 minutes. A synthetic voice reads the article and announces each section title as it begins; tables are read row by row and the questions at the end are left out.
Recorded 19 October 2026 from the article as published that day. Press a chapter to jump there; the highlighted line is what is playing. A play button sits beside every section heading, and once you scroll past this player a bar at the bottom of the screen keeps the controls in reach. Tap or click any sentence to hear the reading start from there.
On this page: a table of how often two IVF trials and four product labels record discharge on each progesterone route, what to call the clinic about, and a checklist for living with pessaries.
Think you already know this? Five questions, one minute.
Every answer is on this page. Answer from what you know now; the page fills in the rest.
-
1. Why do vaginal progesterone pessaries cause heavy discharge?
The base of the medication melts at body temperature: some is absorbed, and the rest leaves as residue. The patient leaflet for Cyclogest 400mg pessaries lists this leakage as quite normal. Read the section
-
2. Why is discharge not a reliable sign of whether an embryo has implanted?
The pessaries leave residue whatever the outcome, and the product labels, such as the Crinone US label, list discharge as an effect of the medicine rather than of pregnancy. Read the section
-
3. In the two IBSA trials posted on ClinicalTrials.gov, what happened to discharge reports when progesterone was given by injection instead of vaginally?
Discharge was logged in 60 of 344 women on vaginal gel against 13 of 338 on injections in trial NCT00827983, and in 50 of 400 on vaginal tablets against none of 400 on injections in trial NCT00828191. Read the section
-
4. Which symptom is a reason to contact your clinic rather than treating it yourself?
Green or grey discharge, or discharge accompanied by itching, burning, or a strong smell, suggests a possible infection that requires clinic-approved treatment. The NHS vaginal discharge page links green or yellow discharge to infections like trichomoniasis. Read the section
-
5. Why does tracking cervical mucus not work the same way during a medicated IVF cycle?
In a medicated cycle, you receive progesterone from the outside on a fixed schedule, meaning your observations track the medication schedule rather than your own cycle’s natural signals. Read the section
It is worth explaining properly though, because knowing the mechanism is more reassuring than being told not to worry, and because there are a small number of things that genuinely are worth a call.
What the pessaries actually do
Vaginal progesterone is delivered in a wax, oil or gel base. That base melts at body temperature, some is absorbed, and the rest leaves. What leaves looks like discharge, and there is often a surprising amount of it.
The manufacturers say as much in their own paperwork, which is rarer than it should be. The UK patient leaflet for Cyclogest 400mg pessaries lists leakage after the pessary has dissolved among its effects and calls it quite normal for any medicine inserted into the vagina. The United States prescribing information for Crinone progesterone gel says small white globules may appear as a discharge, possibly from gel building up, even several days after use. Neither document mentions an embryo, because the discharge has nothing to do with one.
Separately, progesterone itself changes cervical secretions, generally increasing volume and thickening texture. So you are getting both effects at once: residue from the medication, and a genuine hormonal change in what your body produces.
Together those explain thick white discharge, waxy or gritty residue, yellowish tinting, and a general sense that there is far more going on than usual. All of that is expected.
| What you notice | Most likely explanation |
|---|---|
| White or cream, thick | Pessary base plus progesterone effect |
| Waxy or gritty residue | Undissolved pessary base, entirely expected |
| Yellowish tint | Common with pessaries, usually not significant |
| Increased volume generally | Progesterone, reliably |
| Brown tinged | Old blood, often cervical irritation from insertion |
| Green or grey, strong smell | Possible infection, call the clinic |
| With itching or burning | Possible thrush or infection, call the clinic |

Why it is not a sign of implantation
The same reason nothing else in this fortnight is. The cause you are looking for and the cause that is actually operating produce the same observation.
You would have this discharge whether or not an embryo implanted, because the pessaries do not know the outcome and neither does your cervix. The product labels list it as an effect of the medicine, the trials count it as a side effect of the medicine, and neither treats it as a clue to pregnancy, so it distinguishes nothing. The same reasoning applies further down, which is why loose stools and diarrhea in the two week wait carry no more information than discharge does.
This is the third or fourth article on this site to reach the same conclusion, and that repetition is deliberate. Every observation available to you during the wait has a progesterone shaped explanation sitting in front of it. That is why the blood test exists. The same reasoning applied to the most common late wait worry, cramping that feels like a period on the way, is in day 9 after transfer and the period feeling.
How often do trials record discharge on each progesterone route?
This is where the progesterone explanation stops being an assertion and becomes a count. Two luteal support trials run by IBSA, the maker of an injectable progesterone, posted their side effect tables on ClinicalTrials.gov. Each compared a vaginal product with daily injections under the skin, and each recorded vaginal discharge in both groups. Take the vaginal product away and discharge reports almost disappear, even though everyone in both groups was going through the same transfer and the same wait.
| Progesterone route | What was recorded | Source |
|---|---|---|
| Vaginal gel | Vaginal discharge in 60 of 344 women, 17.4 percent | IBSA trial NCT00827983 |
| Injection under the skin, same trial | Vaginal discharge in 13 of 338 women, 3.8 percent | IBSA trial NCT00827983 |
| Vaginal tablets | Vaginal discharge in 50 of 400 women, 12.5 percent | IBSA trial NCT00828191 |
| Injection under the skin, same trial | Vaginal discharge in 0 of 400 women | IBSA trial NCT00828191 |
| Crinone 8% gel twice daily | Vaginal discharge in 7 percent of 61 women | Crinone US label, Table 3 |
| Endometrin vaginal insert | Not among reactions at 2 percent or more in 808 women; irritation, itching, burning and discomfort listed as less common | Endometrin US label, revised July 2026 |
| Cyclogest 400 mg pessary | Soreness and some leakage of the pessary base listed, no rate given | Cyclogest SmPC, revised 13 December 2023 |
| Utrogestan Vaginal 200 mg capsule | Oily discharge from the vagina, frequency not known | Utrogestan Vaginal leaflet, revised March 2024 |
Two cautions before anyone builds a theory on the decimals. The Endometrin label says rates from one drug’s trials cannot be directly compared to rates in the trials of another, and the products here were tested in different studies with different counting. And the two registry trials were paid for by the company selling the injection, which had every reason to notice what the vaginal products did. Neither caution touches the main point: within each trial, the same kind of patient on the same kind of wait reported discharge far more often when the progesterone went in vaginally.
What the tables do not say matters as much. None of these documents links discharge to whether a pregnancy followed, and none of them offers a discharge that belongs to implantation. If your clinic chose a vaginal route, more discharge is the expected price of that route, and your clinic knows which product you are on and why.
How it changes across the fortnight
People often expect a pattern and then read meaning into whatever shape appears. It is worth knowing that the shape is mostly determined by the medication schedule.
In the first days after transfer you may notice residue from the transfer procedure itself alongside the pessaries. Through the middle of the wait, the pessary effect dominates and tends to be fairly constant, because you are taking the same thing at the same intervals. Toward the end, nothing about the discharge changes to announce the result, which disappoints people who were waiting for a signal.
So a change across the fortnight usually reflects something practical: a missed dose, a different insertion time, a new formulation, more or less activity. It very rarely reflects anything about the embryo.
If you are on injections instead
Not everyone uses vaginal progesterone. Some protocols use intramuscular injections, and some use a combination.
If you are on injections only, the heavy discharge described above will largely not apply to you, because there is no pessary base to leave residue. You may still notice some increase from progesterone acting on the cervix, and it will be far less dramatic. Injections bring their own nuisances instead, mainly soreness and lumps at the injection site. Skin reactions at the injection site are among them, and our page on what the leaflets say causes a so called implantation rash sets out how often each medicine lists them.
Which route you are on is worth knowing when you read anything about the two week wait, including this article, because a great deal of the advice online assumes pessaries without saying so.
The things that genuinely warrant a call
A short list, and none of them are about volume.
- Green or grey discharge
- A strong or unpleasant smell
- Itching, burning or soreness
- Discharge alongside pelvic pain or a fever
- Anything that worries you enough to have read this far
The first four suggest infection rather than a hormonal change. Infections during a cycle are treatable and worth treating, and clinics would much rather hear about one early. Do not treat it yourself, because what is safe alongside your medication is their call rather than a pharmacist’s.
For reference, the NHS vaginal discharge page, reviewed on 15 February 2024, describes normal discharge as clear or white, thick and sticky or slippery and wet, without a strong smell, and links a fishy smell to bacterial vaginosis, a thick white cottage cheese texture to thrush, and green, yellow or frothy discharge to trichomoniasis. Notice the awkward overlap. Thick and white is the thrush description and also the pessary description, so during a medicated cycle texture on its own settles nothing either way. Itching, soreness, burning or a smell are what tip it towards a call, and during a cycle that call goes to the clinic rather than to a pharmacy counter. Our page on whether implantation bleeding has a smell sets those NHS smell markers beside the progesterone leaflets, neither of which mentions odour at all.
Heavy bleeding that soaks a pad, severe or worsening pain, a fever, shortness of breath, sudden severe bloating, or vomiting you cannot keep on top of. Those are reasons to phone the clinic now rather than to search. Clinics expect these calls and would far rather hear from you early.
A note on comparing with a natural cycle
If you have tracked cervical mucus before, either while trying naturally or out of habit, you may be trying to read this fortnight the same way. It does not translate.
In a natural cycle, changes in discharge follow your own hormones and can be genuinely informative about where you are. In a medicated cycle you are receiving progesterone from outside on a fixed schedule, so what you observe tracks the schedule rather than your cycle. The signal you learned to read is being overwritten by the medication.
That is worth knowing because people who are good at body literacy often find this fortnight especially frustrating. A skill that usually gives you information has been switched off, and no amount of attention will switch it back on.
Practical things that make it easier
- Use a liner rather than a tampon, always, throughout the wait.
- Expect more residue with some formulations than others. It is not a sign the medication is not working.
- Insert pessaries at consistent times, and ask your clinic whether lying down briefly afterwards is worth doing with your particular product.
- If soreness develops, mention it at your next contact rather than waiting for it to become a problem.
- Do not compare what you are seeing with photographs online. It will not tell you anything and it will make the day worse.
Practical Steps for Managing Discharge
Use this checklist to help manage the physical effects of progesterone pessaries comfortably during your two week wait.
Ticks are saved on this device only.
What actually answers the question
The blood test, on the date your clinic set. the beta test covers what it measures and why the number matters less on its own than people expect.
If what you are seeing is more blood than discharge, brown spotting covers brown spotting specifically and telling bleeding apart from a period covers the comparison with a period. For the wider picture, what symptoms can and cannot tell you is the honest version.
Frequently asked questions
Is increased discharge a sign of implantation?
No. If you are using vaginal progesterone, the pessaries themselves produce a great deal of discharge, both from the medication base and from the effect of progesterone on the cervix. That is by far the most likely explanation and it happens regardless of outcome.
What does the white residue mean?
It is usually the pessary base rather than anything your body produced. Vaginal progesterone comes in a wax or oil carrier that melts, is absorbed partially, and leaves the rest behind. Seeing it is expected and means the medication is where it should be.
What colour of discharge is a concern?
Green or grey, anything with a strong or unpleasant smell, or anything accompanied by itching, burning or soreness. Those suggest an infection rather than a hormonal change and are worth a call, because infections are treatable and worth treating.
Can progesterone cause thrush?
It is a recognised nuisance of vaginal progesterone, and the symptoms are itching, soreness and a change in texture. Do not treat it yourself during a cycle. Ask the clinic, because they will want to advise on what is safe alongside your medication.
Should I stop using pessaries if discharge is heavy?
No. Never stop or alter medication on your own during a cycle. Heavy discharge is expected with pessaries and stopping support can cause real harm. If it is bothering you, call and ask rather than deciding.
Does watery discharge mean anything?
Not on its own. If you are ever unsure whether you are seeing discharge or fluid loss, particularly later in a pregnancy, that is a question for the clinic rather than for a website.
Finished the page? The same five questions from the top, to see what stuck.
This article is general information, not medical advice, and is not a substitute for care from a qualified healthcare professional. Speak to your doctor about your own situation.
Leave a Reply