
Early pregnancy light bleeding after IVF is common, and it is listed as a recognised effect of the vaginal progesterone most people are still taking at this point. That does not make it harmless, and it does not make it a sign. Tell your clinic about any bleeding, and treat heavy bleeding or pain as urgent.
Listen to this article, about 10 minutes. A synthetic voice reads the article and announces each section title as it begins; tables are read row by row and the questions at the end are left out.
Recorded 4 October 2026 from the article as published that day. Press a chapter to jump there; the highlighted line is what is playing. A play button sits beside every section heading, and once you scroll past this player a bar at the bottom of the screen keeps the controls in reach. Tap or click any sentence to hear the reading start from there.
On this page: what the progesterone labels actually list, the cohort of 4,510 pregnancies that separates light spotting from heavy bleeding with pain, two IVF facts that look contradictory and are both true, what four forum threads show, and the exact thresholds for urgent care.
Think you already know this? Five questions, one minute.
Five questions on what the labels, the cohort and the guidance say. None of them are about your own pregnancy.
-
1. On the Endometrin label, how often was vaginal bleeding reported during luteal support in ART?
The FDA label via DailyMed gives 3 percent on both regimens. Crinone’s table only shows events at 5 percent or more, and the UK Cyclogest summary rates bleeding as uncommon. The labels cannot be lined up against each other, and none of it is a reason to change anything you take. Read the section
-
2. In the Hasan 2009 cohort of 4,510 pregnancies, what was the odds ratio for miscarriage with spotting alone?
The study in Obstetrics and Gynecology found no detectable difference for spotting or for any bleeding. Heavy bleeding, and heavy bleeding with pain, were different, at 2.84 and 4.79. It is a population statistic and says nothing about one pregnancy. Read the section
-
3. What did Perkins and colleagues find about the ectopic rate in 553,577 ART pregnancies?
The dataset shows 1.7 percent against around 2 percent generally. Heterotopic pregnancy is the different matter, rare but considerably more common after assisted reproduction, which is why clinics want to hear about bleeding and pain even after a good scan. Read the section
-
4. What did the four Mumsnet threads show about the forum rule that brown is reassuring and red is alarming?
Same medication, same thread, opposite outcomes: one poster’s scan found a heartbeat after orange red bleeding, another’s found the pregnancy had stopped after brown bleeding, and one had no bleeding at all before a missed miscarriage. Neither presence nor absence carries information. Read the section
-
5. Which of these is on the NHS list for calling 999 in pregnancy?
The NHS guidance lists severe pain you cannot see past, shoulder pain, feeling sick, faint or dizzy, losing consciousness, and soaking a pad soon after putting it on. Below that, contact your early pregnancy unit or 111 for any bleeding before 20 weeks, and your fertility clinic as the extra call. Read the section
This page is about bleeding after a positive test, once a beta has come back and you are still on luteal support. That is a different situation from spotting during the two week wait, when nobody knows anything yet. If you have not tested, implantation bleeding or period is the article you wanted and this one will not help.
The national health service pages that rank for this search are accurate and were written for someone who conceived without help. That reader is not on progesterone, does not know her implantation date to the day, and has not had a transvaginal probe near her cervix recently. You are, you do, and you probably have.
What counts as light bleeding at this stage?
Light means spotting: a pink, red or brown mark noticed on wiping, or a few spots a liner absorbs without complaint. Not a flow, not a pad that fills. Heavier than that is a different question, answered further down under urgent care.
The internet will offer you a colour chart. Brown is old and therefore fine, red is fresh and therefore bad, and somewhere a shade guide that reads like a paint catalogue. No label, guideline or study makes that distinction. Colour tells you roughly how long blood took to leave and nothing about why it was there. More in what implantation bleeding looks like. How that plays out during the wait itself, before any test, is covered in what brown spotting after a transfer can and cannot mean.
Why does progesterone change how bleeding reads after IVF?
Because it is on the label. Every widely used vaginal progesterone preparation for luteal support lists bleeding among its recognised effects, and the pages ranking for this search do not mention any of them. Here is what the regulators actually publish.
| Preparation | Label | Bleeding entry for luteal support in ART | Reported frequency |
|---|---|---|---|
| Endometrin 100 mg vaginal insert | FDA label via DailyMed | Vaginal bleeding | 3 percent on twice daily and 3 percent on three times daily, 404 women per arm |
| Crinone 8 percent vaginal gel | FDA label via DailyMed | No bleeding entry in the IVF luteal support table | That table reports only events occurring in 5 percent or more of 139 women |
| Cyclogest 400 mg pessary | UK summary of product characteristics | Vaginal haemorrhage and metrorrhagia | Uncommon, between 1 in 1,000 and 1 in 100 |
Those figures cannot be lined up against each other. Crinone’s table looks clean only because it was built to show events at 5 percent and above, so a 3 percent event would never appear in it. What the labels agree on is the part that matters: bleeding on this medication is documented and unsurprising, and it is absent from every general pregnancy page you have read tonight.
None of that is a reason to change anything you are taking. How and whether you take luteal support is a decision for the clinic that prescribed it and holds your notes. This site has no view on your protocol and could not form one.

Does light bleeding change the odds either way?
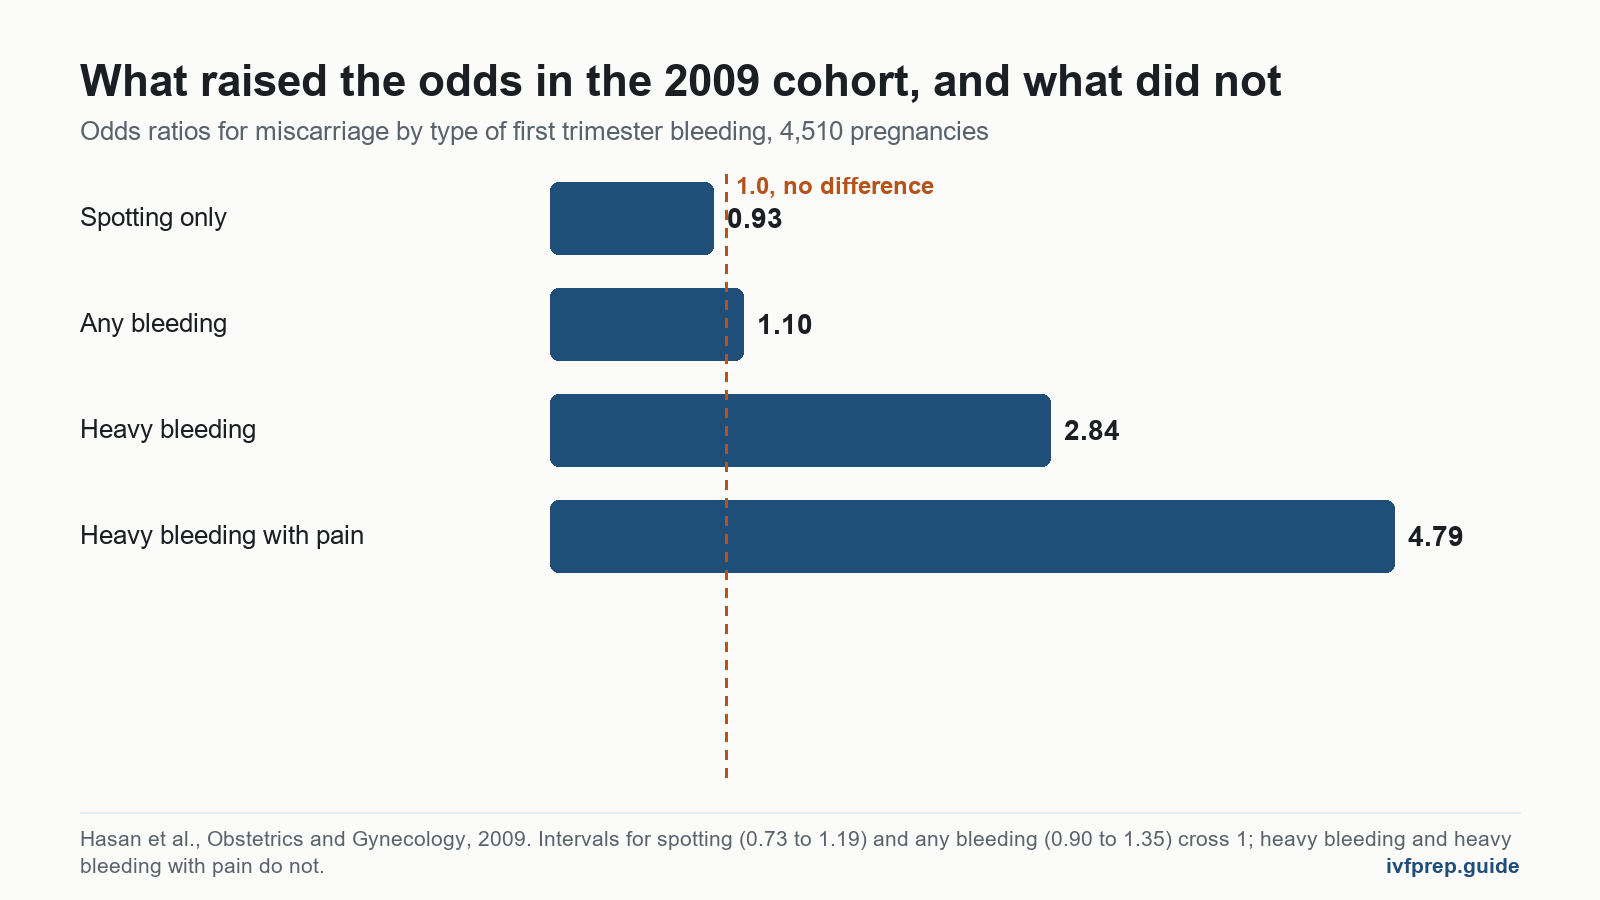
The cleanest answer comes from a community based cohort of 4,510 pregnancies published in Obstetrics and Gynecology in 2009 by Hasan and colleagues. About 27 percent of them, 1,204 women, reported first trimester bleeding or spotting. The odds ratio for miscarriage with any bleeding was 1.10, interval 0.90 to 1.35. For spotting alone it was 0.93, interval 0.73 to 1.19. Both intervals cross 1, which means the study could not detect a difference.
The same paper found something different for heavy bleeding: an odds ratio of 2.84, interval 1.82 to 4.43, and for heavy bleeding accompanied by pain, 4.79, interval 2.97 to 7.73. That is the real dividing line, and it is about volume and pain, not colour and not timing. It is also a population statistic. It describes thousands of pregnancies and says nothing about yours, which is the frustrating shape of every honest answer on this topic.
Two facts about IVF specifically look contradictory and are both true. In 553,577 ART pregnancies in the United States, Perkins and colleagues found an ectopic rate of 1.7 percent, similar to the general population figure of around 2 percent, so the widely repeated line that IVF greatly raises ectopic risk is not what that dataset shows. Heterotopic pregnancy, where one embryo implants in the uterus and another outside it, is a different matter: a 2022 review in Frontiers in Medicine puts it between 1 in 7,963 and 1 in 30,000 in spontaneous pregnancies, and between roughly 1 in 100 and 1.5 in 1,000 after assisted reproduction. A scan showing a pregnancy in the right place does not entirely close that question, which is why your clinic wants to hear about bleeding and pain even after a good scan.
What do people on progesterone actually report?
Forum accounts are testimony, not evidence, and nothing below is a finding about anyone’s pregnancy including your own. They are worth reading because they show the range, and the range is the point. Four public Mumsnet threads, 63 replies between them, all on bleeding while taking progesterone pessaries.
On a pregnancy board thread from August 2022 with 36 replies, the original poster described a small amount of orange red blood at five weeks on Cyclogest and asked whether it was normal. She returned ten days later to say a scan at eight and a half weeks had found a heartbeat. Another poster in the same thread described bleeding at seven, nine and ten weeks with normal scans each time, writing at 39 weeks pregnant. Further down, a third described heavier brown bleeding at just past nine weeks, and her scan found the pregnancy had stopped at eight. Same medication, same thread, opposite outcome. Anyone who tells you the boards lean reassuring stopped reading at the top of the page.
On a separate pregnancy thread from August 2023 with 12 replies, two posters on the same preparation described spotting after a positive test, and both said their clinic wanted to know and changed their prescription. What that change was is between them and their clinic, and it is not a template for anyone else.
The account that reframes the question sits on the miscarriage board, November 2020, with 7 replies. That poster had an IVF pregnancy, no bleeding at all, and learned at a seven week scan that it had stopped growing at six. Several replies said the same: nothing happened until the progesterone was stopped. So the medication can quieten bleeding as well as cause it, which means neither the presence of blood nor its absence carries information. That is the argument this site keeps making in no bleeding, no symptoms, and it holds after a positive test as firmly as before one.
Where the accounts and the guidance agree: everyone who bled reported it and everyone was assessed. Where they diverge: the forum convention that brown is reassuring and red is alarming appears in no label and no guideline, and these four threads contain counterexamples in both directions.
When does bleeding after IVF need urgent care?
The NHS guidance on vaginal bleeding in pregnancy says to call 999 if you are bleeding and have severe pain in your tummy, meaning pain you cannot see past to read or watch anything, or pain in your shoulder, or if you feel sick, faint or dizzy or lose consciousness, or if the bleeding is heavy enough to soak a period pad soon after putting it on. Those are the thresholds. They do not change because you conceived through IVF.
Below that threshold, the NHS advice is to contact your maternity unit, early pregnancy unit or NHS 111 for any bleeding or spotting before 20 weeks. Your fertility clinic is the extra call in your case, because it holds your protocol, your dates and your scan history. Clinics differ on how they want to be contacted out of hours, so the number on your paperwork beats anything here.
Shoulder tip pain is worth knowing by name. It does not feel like a gynaecological symptom and it is on the emergency list. Our article on clots in the two week wait covers the same thresholds for the earlier phase.

What is worth writing down before you call?
Clinics ask the same questions every time, and answering from memory at two in the morning is harder than it sounds. This list is built from what the guidance above actually asks about: volume, pain and timing, and pointedly not colour.
- How much, in pads or liners rather than adjectives: a liner marked, a liner soaked, a pad changed at a normal rate, or a pad soaked within an hour.
- Whether there is pain, where it is, whether it is on one side, and whether it stops you doing ordinary things.
- Any shoulder pain, dizziness or faintness.
- When it started, how long it has run, and whether it has been continuous or in episodes.
- Which luteal support you are on, the dose, and how you take it.
- The date of your positive beta, any repeat values, and the date and finding of any scan.
Written once, it doubles as a record if the bleeding comes back, which spares you reconstructing last Tuesday from memory at four in the morning.
Before you call, from this page
Built from what the guidance actually asks about: volume, pain and timing, and pointedly not colour. Written once, it doubles as a record if it comes back.
Ticks are saved on this device only. Heavy bleeding, severe pain, shoulder pain or feeling faint are 999, not a list.
Frequently asked questions
Can light bleeding after a positive beta be caused by progesterone pessaries?
Bleeding is listed on the labels of the vaginal progesterone preparations used for luteal support in IVF, including a 3 percent rate on the Endometrin label and an uncommon rating on the UK Cyclogest summary of product characteristics. That means it is a recognised effect, not that it explains any particular episode. Your clinic decides what is behind yours.
Should I stop my progesterone if I start bleeding?
That is not a decision this page can weigh in on, and nothing here should be read as a reason to change anything. Call the clinic that prescribed it. They hold your protocol, your dates and your results, and they are the only people who can answer it.
Does brown blood mean something different from red blood?
Colour tells you roughly how long blood took to leave, not what caused it. No drug label or national guideline sorts outcomes by colour, and the forum convention that brown is reassuring has counterexamples in both directions. Volume and pain are what the guidance actually asks about.
Is bleeding more common after IVF than in other pregnancies?
It is commonly reported to be, and the extra causes are easy to list: luteal support, recent instrumentation and a higher rate of multiple pregnancy. We were unable to open a study comparing the two populations directly, so treat the comparison as widely stated rather than verified here.
I have already had a scan showing the pregnancy in the right place. Do I still need to report bleeding?
Yes. Heterotopic pregnancy, where one embryo implants inside the uterus and another outside it, is rare but considerably more common after assisted reproduction than after spontaneous conception, and a scan showing an intrauterine pregnancy does not rule it out. Report bleeding and pain.
How long does light bleeding in early pregnancy usually last?
Spotting described in the forum accounts ranged from a single episode to intermittent bleeding over several weeks, and the accounts covered every outcome. There is no duration that sorts one from another, which is why the guidance asks you to report it rather than time it.
Finished the page? The same five questions from the top, to see what stuck.
This article is general information, not medical advice, and is not a substitute for care from a qualified healthcare professional. Speak to your doctor about your own situation.
Leave a Reply