
Brown blood implantation is something nobody can confirm by looking. After an embryo transfer, brown spotting is usually older blood, most often put down to vaginal progesterone or the transfer itself, and it cannot tell you whether the cycle worked. Heavy bleeding, bleeding with severe pain, or feeling faint is a reason to phone the clinic.
Listen to this article, about 12 minutes. A synthetic voice reads the article and announces each section title as it begins; tables are read row by row and the questions at the end are left out.
Recorded 4 October 2026 from the article as published that day. Press a chapter to jump there; the highlighted line is what is playing. A play button sits beside every section heading, and once you scroll past this player a bar at the bottom of the screen keeps the controls in reach. Tap or click any sentence to hear the reading start from there.
On this page: the correction this page owed its readers, a table of the four sources that actually measured bleeding before the test with what each cannot tell you, ten forum accounts read for the one that usually goes missing, and a log for what you saw and what the clinic said.
Think you already know this? Five questions, one minute.
Every answer is on this page. Answer from what you know now; the page fills in the rest.
-
1. What does the colour of spotting mostly reflect, according to this page?
Brown is older, oxidised blood and red is fresher; the NHS page on bleeding in pregnancy lists pink, red and brown without treating any colour as a sign. Read the section
-
2. What did the 2003 study that dated implantation from daily urine samples find about bleeding?
Harville and colleagues studied 221 women conceiving naturally and found no support for the idea that implantation produces bleeding. Read the section
-
3. In the 2009 study of 292 fresh transfer cycles, how often was bleeding before the test reported on vaginal gel compared with injections?
Per Jabara and colleagues, which counted any spotting reported to the clinic and did not separate brown from red. Read the section
-
4. Why do forum threads about spotting after transfer lean towards stories that ended well?
The record is filtered by who chooses to post; in the August 2023 Mumsnet thread the negative result is the reply that usually goes missing elsewhere. Read the section
-
5. Which of these does the page treat as more important than the colour?
Heavy bleeding, severe pain, shoulder pain or feeling faint are reasons to phone, and in a confirmed pregnancy the NHS says to call 999 for them. Read the section
If you are reading this having just been to the bathroom and felt your stomach drop, that reaction is completely ordinary. What follows is what is most likely happening, what the few studies on bleeding before the test actually found, and what the colour can and cannot tell you. Checked against the sources linked below on 4 October 2026.
What does brown rather than red tell you?
Colour is mostly about time. Fresh blood leaving the body quickly looks red. Blood that has taken longer, and has oxidised on the way, looks brown. The NHS page on vaginal bleeding in pregnancy lists pink, red and brown as the colours spotting comes in, without ranking them as signs of anything.
So brown generally means older, and older generally means whatever caused it happened some time ago rather than right now. That is why people tend to find brown less alarming than red, although no label or guideline treats either colour as a sign. The same logic applied to pink, red and volume is in what implantation bleeding looks like, by colour and amount.
What causes brown spotting after a transfer?
| Cause | When it tends to appear | How common |
|---|---|---|
| Progesterone pessaries irritating the cervix | Any time during the wait | The most common explanation |
| The transfer catheter | First few days after transfer | Common |
| Old blood after egg collection | Earlier in a fresh cycle | Common in fresh cycles |
| A sensitive cervix | Any time, often after intercourse or exercise | Common |
| Implantation | Around the expected window | Possible, not distinguishable |
| Start of a period | Later in the wait, usually becoming red | Possible |
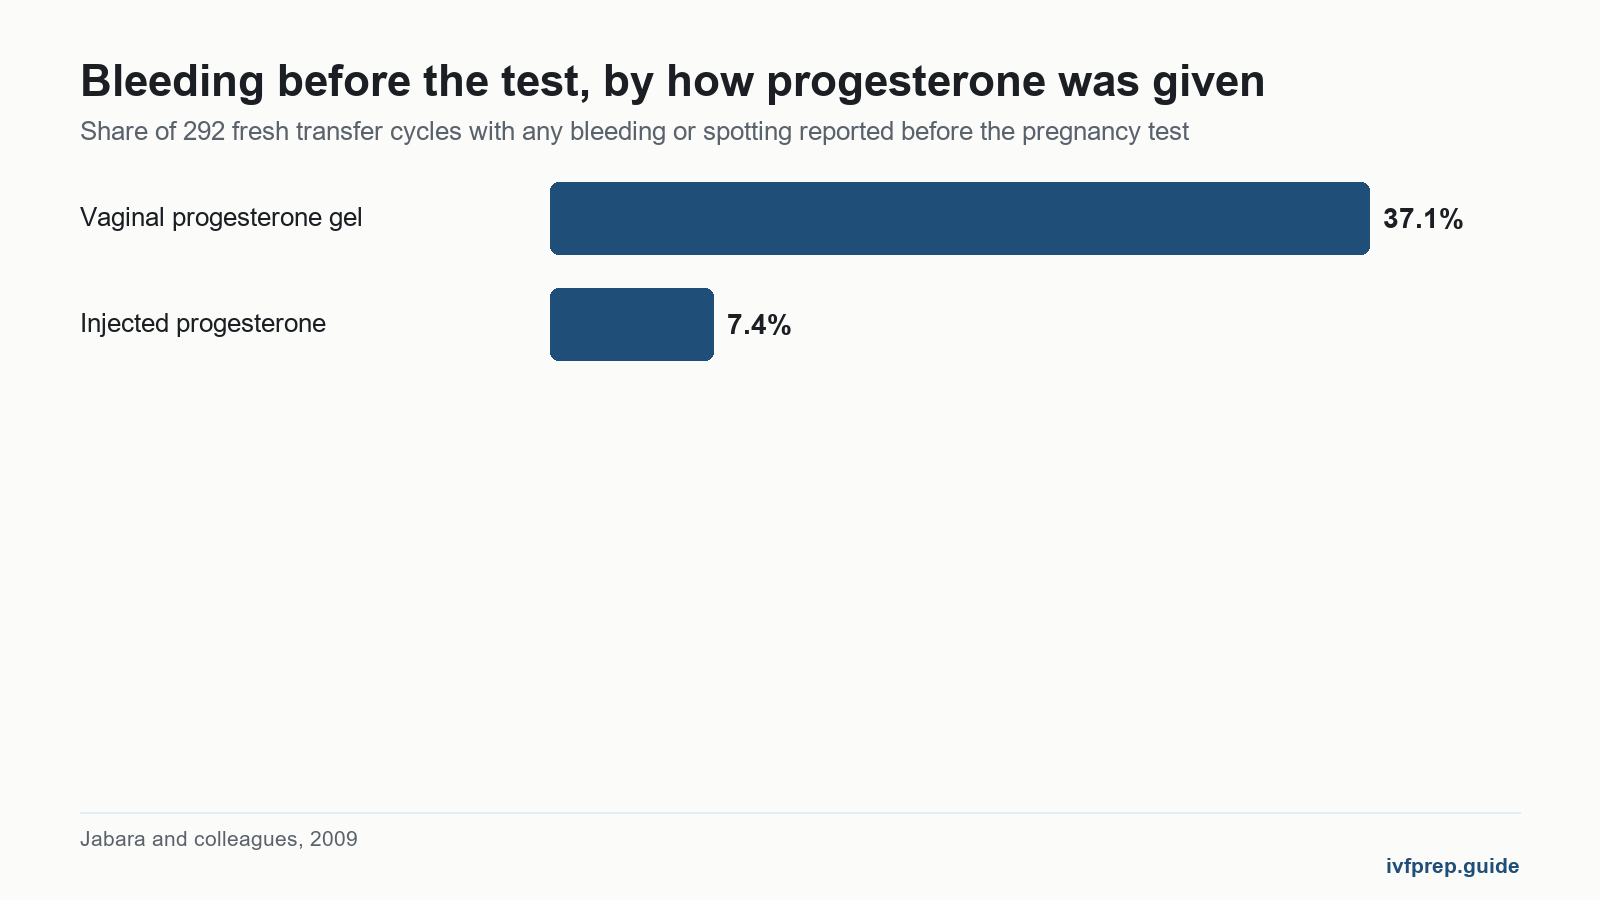
The first row is the explanation clinics give most often, and there is some numerical support for it: in the study tabled further down, bleeding before the pregnancy test was reported in 37.1 percent of cycles on vaginal progesterone gel and 7.4 percent on injected progesterone. Pessaries and gels are inserted vaginally and they irritate. Spotting from that is local and mechanical, nothing to do with the uterus or an embryo. Nobody has measured how much of any one person’s spotting comes from which row, which is the point of the next section.

Is brown blood implantation, or can anyone tell?
Nobody can tell, and not for want of trying. Every cause in that table produces something that looks the same, and they overlap on colour, timing and amount. Timing is the one people most want to lean on, and why a day count cannot sort the causes either is set out in what spotting around 12 DPO means after a transfer.
The idea of a recognisable implantation bleed is itself shakier than the forums suggest. A prospective study in Human Reproduction by Harville and colleagues in 2003 dated implantation from daily urine samples in 221 women and found most bleeding episodes fell at least five days away from it, which gave the authors no support for the idea that implantation produces bleeding at all. That was natural conception rather than IVF, but it is the best timing evidence there is.
What do the studies say about bleeding before the test?
This page used to say that spotting turns up at similar rates whether or not a cycle works. That was wrong, and the honest version is below. The research is thin, old and mostly about fresh transfers, but where people who bled were compared with people who did not, the people who bled had lower pregnancy rates on average.
| Source | Who was studied | What it found | What it cannot tell you |
|---|---|---|---|
| Jabara and colleagues, 2009 | 292 fresh transfer cycles at one US centre, 1999 to 2000 | Bleeding before the test in 37.1 percent of cycles on vaginal gel, 7.4 percent on injections. Pregnancy rate 19.4 percent (14 of 72) among those who bled, 58.2 percent (128 of 220) among those who did not | Colour and amount were not recorded separately, so a smear of brown and a red bleed count the same |
| Yanushpolsky and colleagues, conference report | Interim analysis of a randomised trial, gel against injections | Called bleeding before the test a poor sign for ongoing pregnancy whichever progesterone was used | The press release gives no rates, so the size of the difference is not public there |
| Harville and colleagues, 2003 | 221 women conceiving naturally, implantation dated from urine | Most bleeding fell at least five days from implantation | Not an IVF population and no progesterone support |
| Cyclogest product information | Trial data for 400 mg pessaries as luteal support | Vaginal haemorrhage and bleeding between periods listed as uncommon side effects | Counts reported side effects, not spotting people never mention |
Read the Jabara row both ways, because both halves are true. Bleeding was linked with a lower rate. And 14 of the 72 people who bled were pregnant, while 92 of the 220 who did not bleed were not. A group average is not a verdict on one cycle, which is why the blood test exists. The two sources also disagree with each other on how common bleeding is on vaginal progesterone, 37.1 percent in one clinic’s records against “uncommon” on the product information, and the likeliest reason is that one counted any spotting reported to the clinic while the other counted side effects logged in a trial.
What do people who have had it report?
We read ten accounts across three Mumsnet threads from 2022 and 2023, plus two Fertility Friends threads from 2016 and 2017 that were too old to use. Of the ten, one ended in a negative test, one never said, and several described bleeding after a positive test, which is a different question. These are what people report, not findings, and the four below are the ones about spotting during the wait itself.
- August 2023: a poster on Mumsnet described light brown spotting mixed with mucus, then pink and red on wiping, about four hours after a frozen transfer. Ten days later the same poster wrote that the test was negative.
- August 2023, the same thread: another poster spotted for two days after transfer and reported positive home tests six days after it.
- April 2023: on a Mumsnet thread about bleeding after transfer, one poster described the lightest pink spotting on day 11 and a positive test afterwards.
- April 2023, the same thread: another saw brown blood the night before testing and reported a positive test the next day.
Notice the shape of that. Threads asking whether spotting can be implantation fill up with replies from people whose story ended well, because they are the ones with a reason to come back and write. The negative in the first account is the reply that usually goes missing. The accounts agree with the official guidance that spotting happens in cycles that work, and they disagree with the Jabara figures only because of who chose to post.
Which changes matter more than the colour?
Not the colour. The amount, the direction of travel, and what comes with it.
- Amount. A small amount when you wipe is different from filling a pad.
- Direction. Settling is different from increasing. Brown turning red matters more than brown alone.
- Pain. Bleeding with severe or worsening pain is a different situation entirely.
- Everything else. Dizziness, faintness, fever, breathlessness. Those change the picture.
Heavy bleeding that soaks a pad, severe or worsening pain, pain in the shoulder, feeling faint or dizzy, a fever, shortness of breath, sudden severe bloating, or vomiting you cannot keep on top of. Those are reasons to phone the clinic now rather than to search. Once a pregnancy is confirmed, the NHS says to call 999 for severe tummy pain, shoulder pain, feeling faint or dizzy, or bleeding heavy enough to soak a pad soon after putting it on. Clinics expect these calls and would far rather hear from you early.
Why do pessaries cause this so often?
Worth understanding properly, because it is the likeliest explanation and knowing the mechanism makes it far less frightening at two in the morning.
Vaginal progesterone is inserted directly, often more than once a day, for the whole wait. The tissue there is already more fragile than usual under hormonal influence, and the physical act of insertion can irritate it. Small amounts of blood from that irritation mix with the residue the pessaries leave behind and appear later, by which time they have oxidised and look brown. The product information for Cyclogest lists soreness and some leakage of the pessary base among its effects, which anyone using them will have noticed without being told.
That is why the spotting often looks worse than it is, why it frequently appears mixed with discharge, and why it comes and goes across the fortnight rather than following any pattern that would match implantation.
What practical things help during the wait?
- Use pads rather than tampons during the wait, and mention any spotting at your next contact with the clinic
- Note roughly when it happens relative to using a pessary, because a consistent relationship is informative and reassuring
- Take a photo only if it helps you describe it to the clinic accurately, not to compare against images online
- Lying down for a short while after inserting a pessary is commonly suggested and is worth asking your clinic about
- If it happens most often after exercise or intercourse, that points at cervical sensitivity rather than anything else

What helps at two in the morning?
This is when most people read an article like this one, and the honest advice is different at that hour.
Nothing you can find will change the situation between now and morning. If you have any of the red flag symptoms listed above, call the out of hours number, because that is what it exists for. If you do not, the useful move is to stop searching, because every additional article at this hour makes it worse rather than better, this one included once you reach the end of it.
Write down what you saw and when, so you can describe it accurately tomorrow. Then try to sleep. That is not dismissive, it is the whole of what is available.
A note for the clinic, not a reading
Write down what you saw and when, so that tomorrow’s phone call starts with facts rather than a memory from two in the morning. Nothing here is interpreted.
A record for your own conversation with the clinic. It does not read any symptom and cannot say anything about the outcome. Kept on this device only.
What should not change because of the spotting?
Your medication, unless the clinic tells you otherwise. Stopping or reducing progesterone because you saw blood is an understandable instinct and the wrong move. In many protocols the prescribed progesterone is what is supporting the lining, the pessaries themselves are a likely cause of what you are seeing, and only the people who wrote your protocol know what yours needs.
Call the clinic and ask. That is what they are there for, and asking costs you nothing but the phone call.
What happens between now and the blood test?
Tell your clinic, then try to put it down. That advice sounds thin, and it is still the only useful move available, because the information you want does not exist until the blood test. What the beta test measures covers what that test will actually tell you. If it helps to know what the clinic is working to, the frozen transfer timeline sets out when each date is decided and why. A negative home test early in the wait settles less than it seems to, and what a negative test at seven days past transfer actually rules out shows the numbers behind that.
If what you are seeing is red rather than brown, or you are trying to work out whether a period is starting, telling it apart from a period covers that comparison and is honest about its limits after IVF. If there is no spotting at all and that is the worry, implantation without any bleeding explains why that is the ordinary experience. What implantation actually feels like covers the wider question of what symptoms can and cannot indicate.
Frequently asked questions
Why is the blood brown rather than red?
Brown generally means older blood that has taken time to leave the body and has oxidised on the way. Fresh bleeding is red. That is why brown is usually the more reassuring of the two, though it is still worth telling your clinic about.
Is brown spotting a good sign after embryo transfer?
It is not a sign either way, and this is the part worth holding on to. It is common after transfer for reasons that have nothing to do with implantation, most often progesterone pessaries. People with successful cycles see it and people with unsuccessful cycles see it.
How long does brown spotting usually last?
Often a day or two, sometimes on and off across the wait, particularly if you are using pessaries. Spotting that turns red, becomes heavier, or comes with pain is different and warrants a call.
Could it be old blood from the egg collection?
In a fresh cycle, yes, that is a genuine possibility in the earlier part of the wait. Procedures involving the cervix and ovaries can leave small amounts of blood that appear later and browner.
Should I stop my progesterone if I see spotting?
No. Never stop or change any medication on your own during a cycle. Call the clinic and ask. Stopping progesterone without instruction can cause real harm, and spotting is not a reason to do it.
Does the amount matter more than the colour?
Yes, generally. A small amount of brown is common. Increasing volume, soaking a pad, clots or accompanying pain are the things that matter, and those are reasons to phone rather than to search.
Finished the page? The same five questions from the top, to see what stuck.
This article is general information, not medical advice, and is not a substitute for care from a qualified healthcare professional. Speak to your doctor about your own situation.
Leave a Reply